Clinical and immunologic features of adult primary antibody deficiency according to IVIGRT exposure
Article information

Abstract
Background/Aims
Primary antibody deficiency (PAD) in adults is increasingly recognized, but remains underdiagnosed and undertreated. We described the clinical and immunologic features of adult patients with PAD according to real-world exposure to intravenous immunoglobulin replacement therapy (IVIGRT) and explored whether the Ajou-PAD score reflects treatment decisions in routine clinical practice.
Methods
We conducted a retrospective cohort study at Ajou University Hospital (January 1, 2020–November 18, 2024), screening adults (age ≥ 18 yr) diagnosed with PAD, and excluding those with IVIGRT exposure before diagnosis. After 1:1 propensity score matching by age and sex, clinical and laboratory findings between the IVIGRT-exposed and -unexposed groups were compared. The discriminatory performance of the Ajou-PAD score, a composite index integrating clinical and immunologic parameters, was evaluated for IVIGRT exposure using receiver operating characteristic analysis.
Results
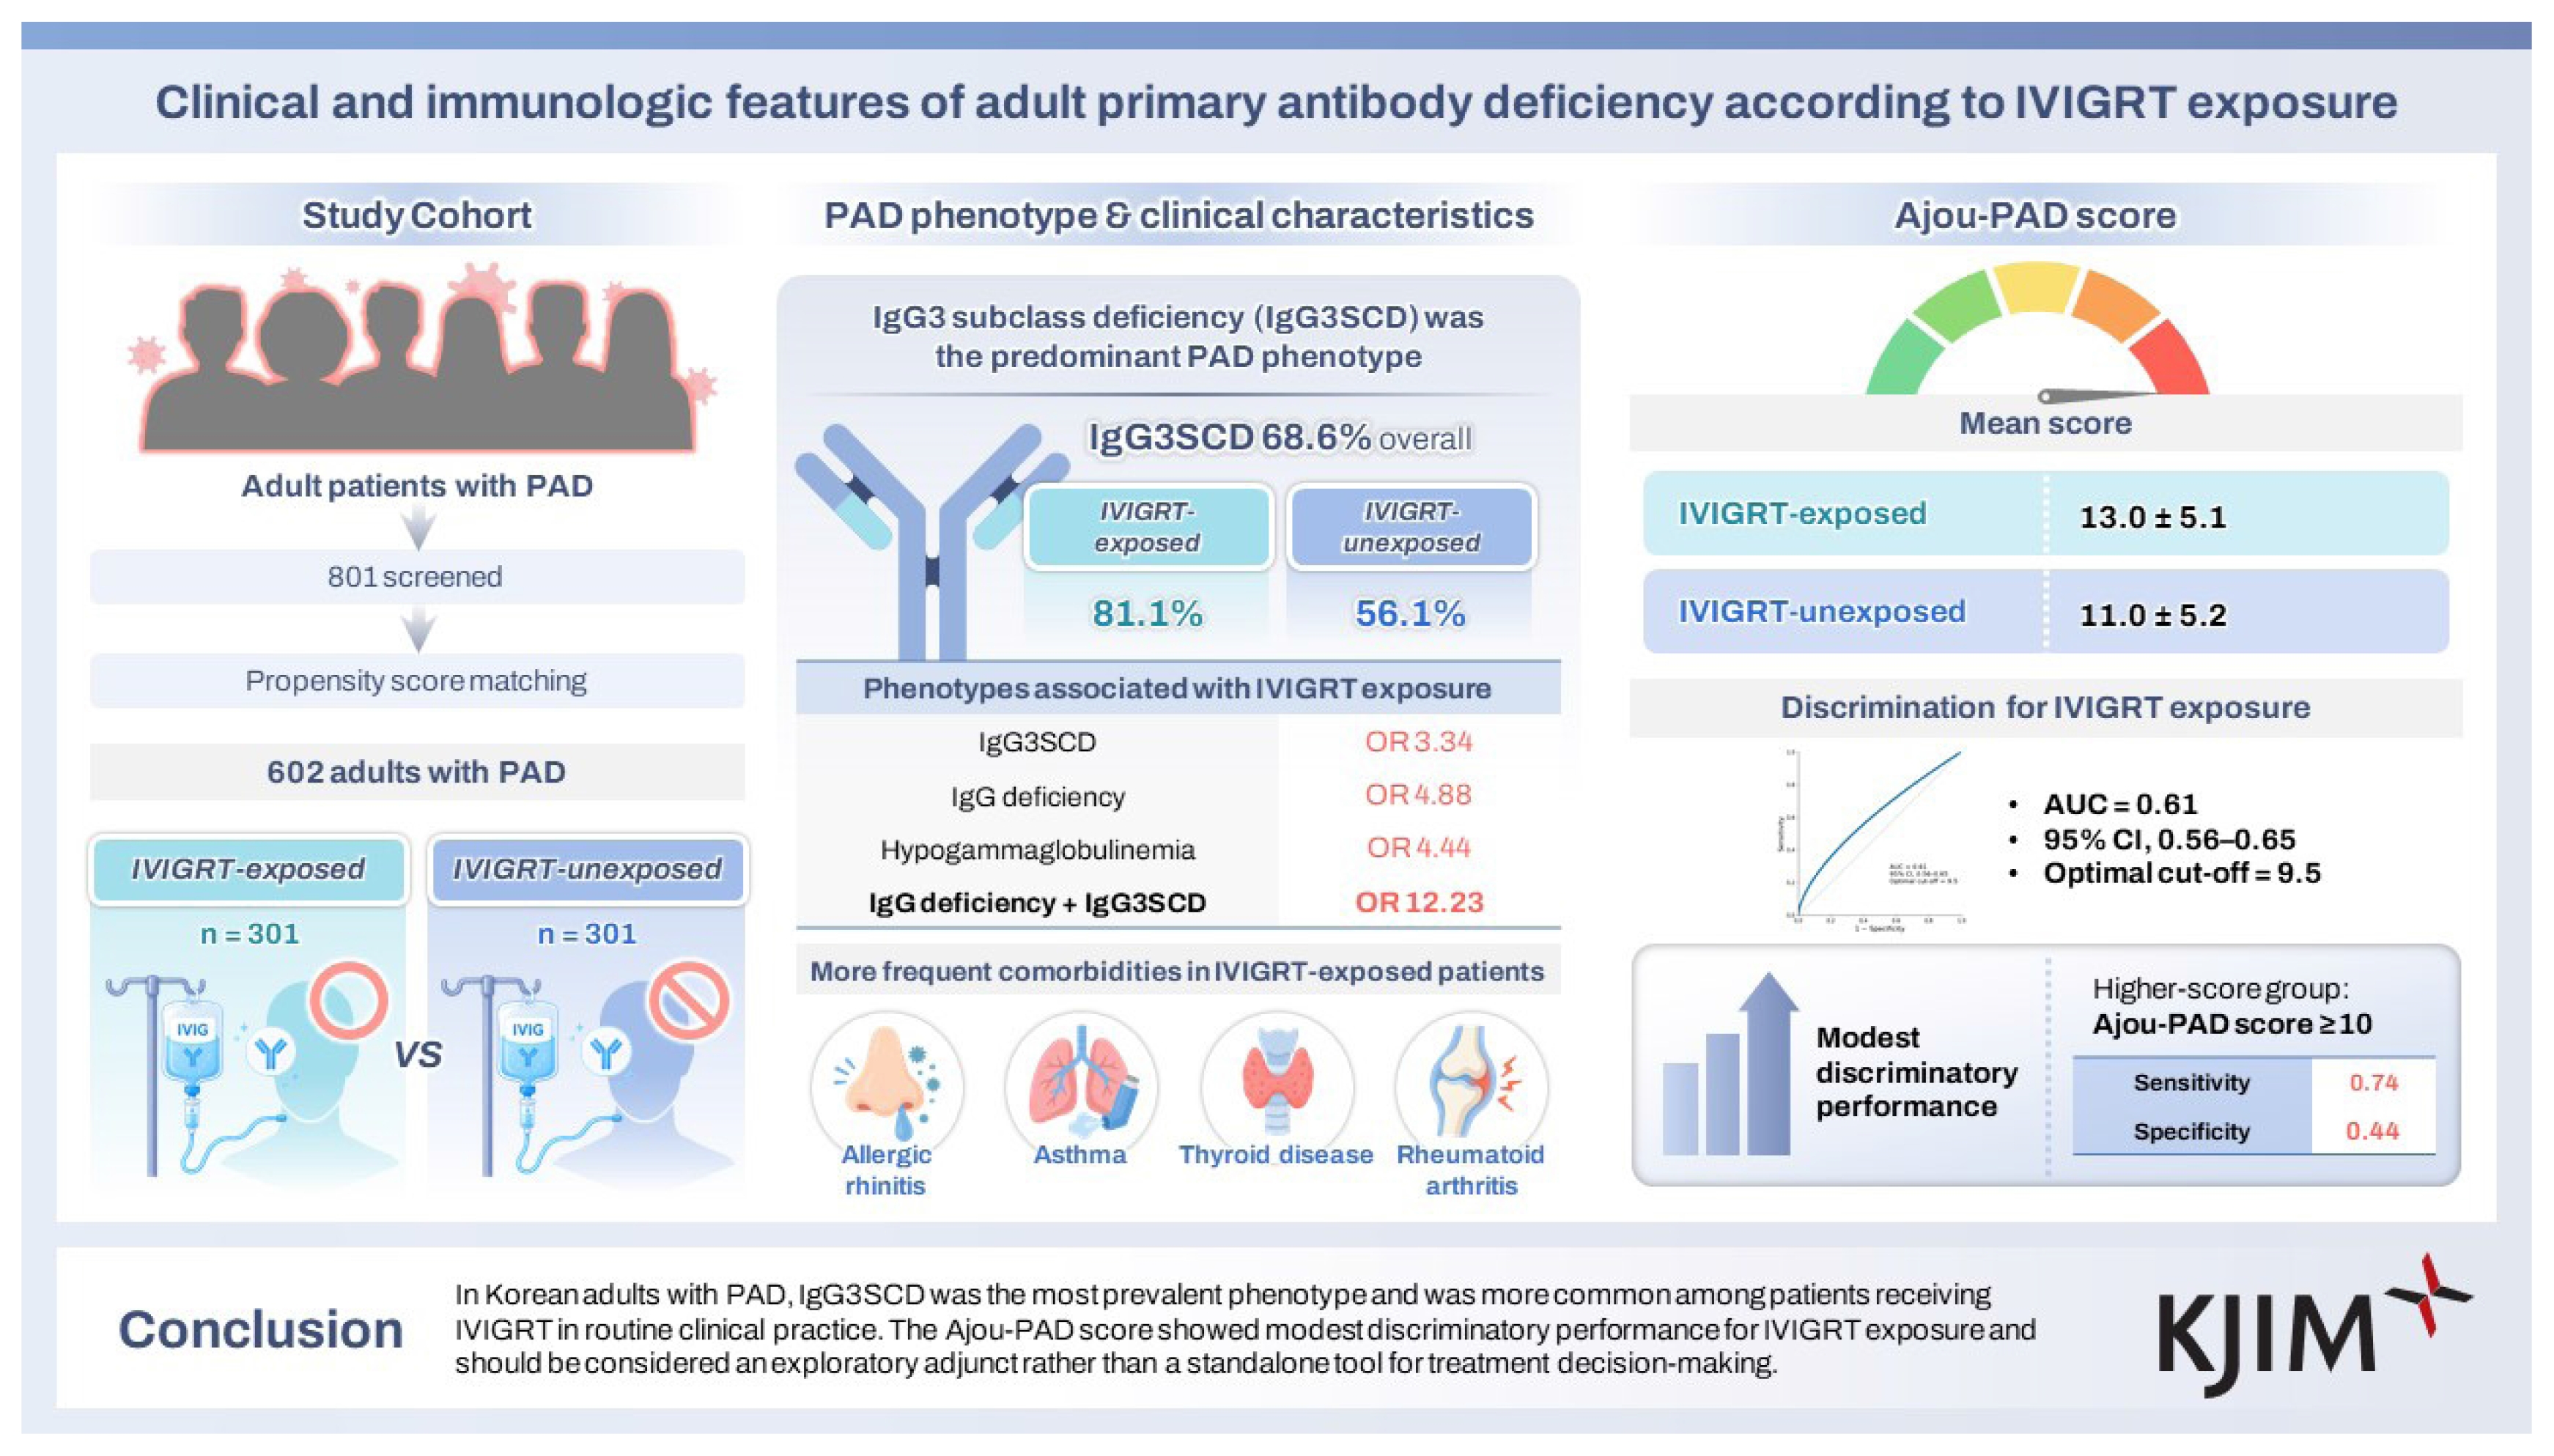
The final matched cohort included 602 patients (301 per group). Immunoglobulin G subclass 3 deficiency (IgG3SCD) was the most prevalent phenotype and more frequent in the IVIGRT-exposed group than in the IVIGRT-unexposed group. The Ajou-PAD score showed modest discriminatory performance for IVIGRT exposure (AUC = 0.61; 95% CI, 0.56–0.65).
Conclusions
In Korean adults with PAD, IgG3SCD was the most prevalent phenotype and was more common among patients receiving IVIGRT in routine clinical practice. The Ajou-PAD score showed modest discriminatory performance for IVIGRT exposure and should be considered an exploratory adjunct rather than a standalone tool for treatment decision-making.
INTRODUCTION
Recent studies suggest an increasing global prevalence of primary antibody deficiency (PAD), a major phenotype of primary immunodeficiency (PID) in adults [1,2]. PAD has traditionally been considered a childhood-onset genetic disorder; however, its manifestation in adults remains underrecognized [3–5]. Adult PAD encompasses a broad spectrum of humoral immune abnormalities, including hypogammaglobulinemia, immunoglobulin G (IgG) subclass deficiency (IgGSCD), and functional antibody deficiency [6–8]. Because IgG subclasses play distinct roles in humoral immunity, deficiencies in specific subclasses may contribute to heterogeneous clinical phenotypes. Accordingly, adult patients with PAD present with heterogeneous clinical features, including variable infectious burden and systemic manifestations [9–11].
PAD diagnosis and management are guided by established international consensus and practice parameters [12,13]. However, the wide clinical heterogeneity of adult PAD often complicates timely diagnosis and treatment decisions [14]. In addition, PAD frequently overlaps with allergic and autoimmune phenotypes [9,15], further delaying appropriate diagnosis and management in real-world clinical practice. Evidence regarding the clinical features and immunologic findings of adult PAD in Korea remains limited. Intravenous immunoglobulin replacement therapy (IVIGRT) is a key therapeutic intervention for patients with PAD, and recent studies suggest potential benefits in selected subgroups, including those with IgG3 subclass deficiency (IgG3SCD) and asthma-related exacerbations [7,8,16]. However, the generalizability of these findings to broader adult PAD populations remains uncertain. Moreover, the optimal timing of IVIGRT initiation—particularly in patients with IgGSCD—remains unclear [17–19]. In clinical practice, IVIGRT initiation is individualized and based on a combination of infection burden, IG levels, comorbid conditions, and functional antibody responses. Although severity scoring systems have been proposed for PID, their utility in guiding treatment decisions in adults with PAD is not well established [20,21].
To address this gap, we developed the Ajou-PAD scoring system by adapting a previously proposed PID severity framework [20] and incorporating symptom burden and laboratory findings to integrate clinical and immunologic parameters, thereby summarizing disease burden and evaluation of its potential to reflect treatment decisions. Accordingly, in this study, we aimed to characterize PAD phenotypes and associated comorbidities according to real-world IVIGRT exposure in a propensity score-matched cohort and to evaluate whether the Ajou-PAD score reflects treatment decisions in routine clinical practice.
METHODS
Study participants and propensity score matching
This retrospective cohort study was conducted at Ajou University Hospital, Korea, from January 1, 2020 to November 18, 2024, and is reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology guidelines [22]. Adults (≥ 18 yr) diagnosed with PAD were identified by review of electronic medical records. PAD phenotypes were classified based on serum IgG, immunoglobulin A (IgA), immunoglobulin M (IgM), and IgG subclass levels using institutional adult reference intervals [23].
PAD phenotypes included hypogammaglobulinemia and IgA, IgM, IgG, and IgG SCDs, defined according to established diagnostic criteria [12,13]. IgG deficiency was defined as total IgG levels below the reference range, whereas hypogammaglobulinemia was defined as broader global IG reduction involving multiple major IG isotypes, including IgG with IgA and/or IgM reduction. To avoid ambiguity with monogenic agammaglobulinemia syndromes, the term agammaglobulinemia was not used as a separate analytic category in this study. Patients with well-defined monogenic immunodeficiencies, including X-linked agammaglobulinemia, were excluded. Patients with secondary causes of antibody deficiency, such as hematologic malignancy, protein-losing conditions, or ongoing immunosuppressive/biologic therapy likely to affect IG levels, were also excluded. IG measurements used for phenotype classification were collected at (or closest to) the time of PAD diagnosis and before IVIGRT initiation. Patients were stratified into two groups according to IVIGRT exposure: those who received at least one course during the study period (IVIGRT-exposed) and those who did not (IVIGRT-unexposed). The IVIGRT-exposed group therefore included both patients who received a single IVIGRT course and those who underwent repeated or long-term IVIGRT during the study period. At our institution, IVIGRT was determined by treating physicians based on clinical factors, including recurrent or severe infections, quantitative IG deficiencies, and relevant comorbidities, with consideration of national insurance reimbursement criteria. Of 801 screened adults, 766 were eligible to participate (IVIGRT-exposed group, n = 413; IVIGRT-unexposed group, n = 353). Propensity score matching (1:1) by age and sex [24,25] yielded 312 matched pairs (n = 624). After excluding 22 patients with IVIGRT exposure before the documented PAD diagnosis, the final analytic cohort comprised 602 adults, with 301 patients in each group (Fig. 1).
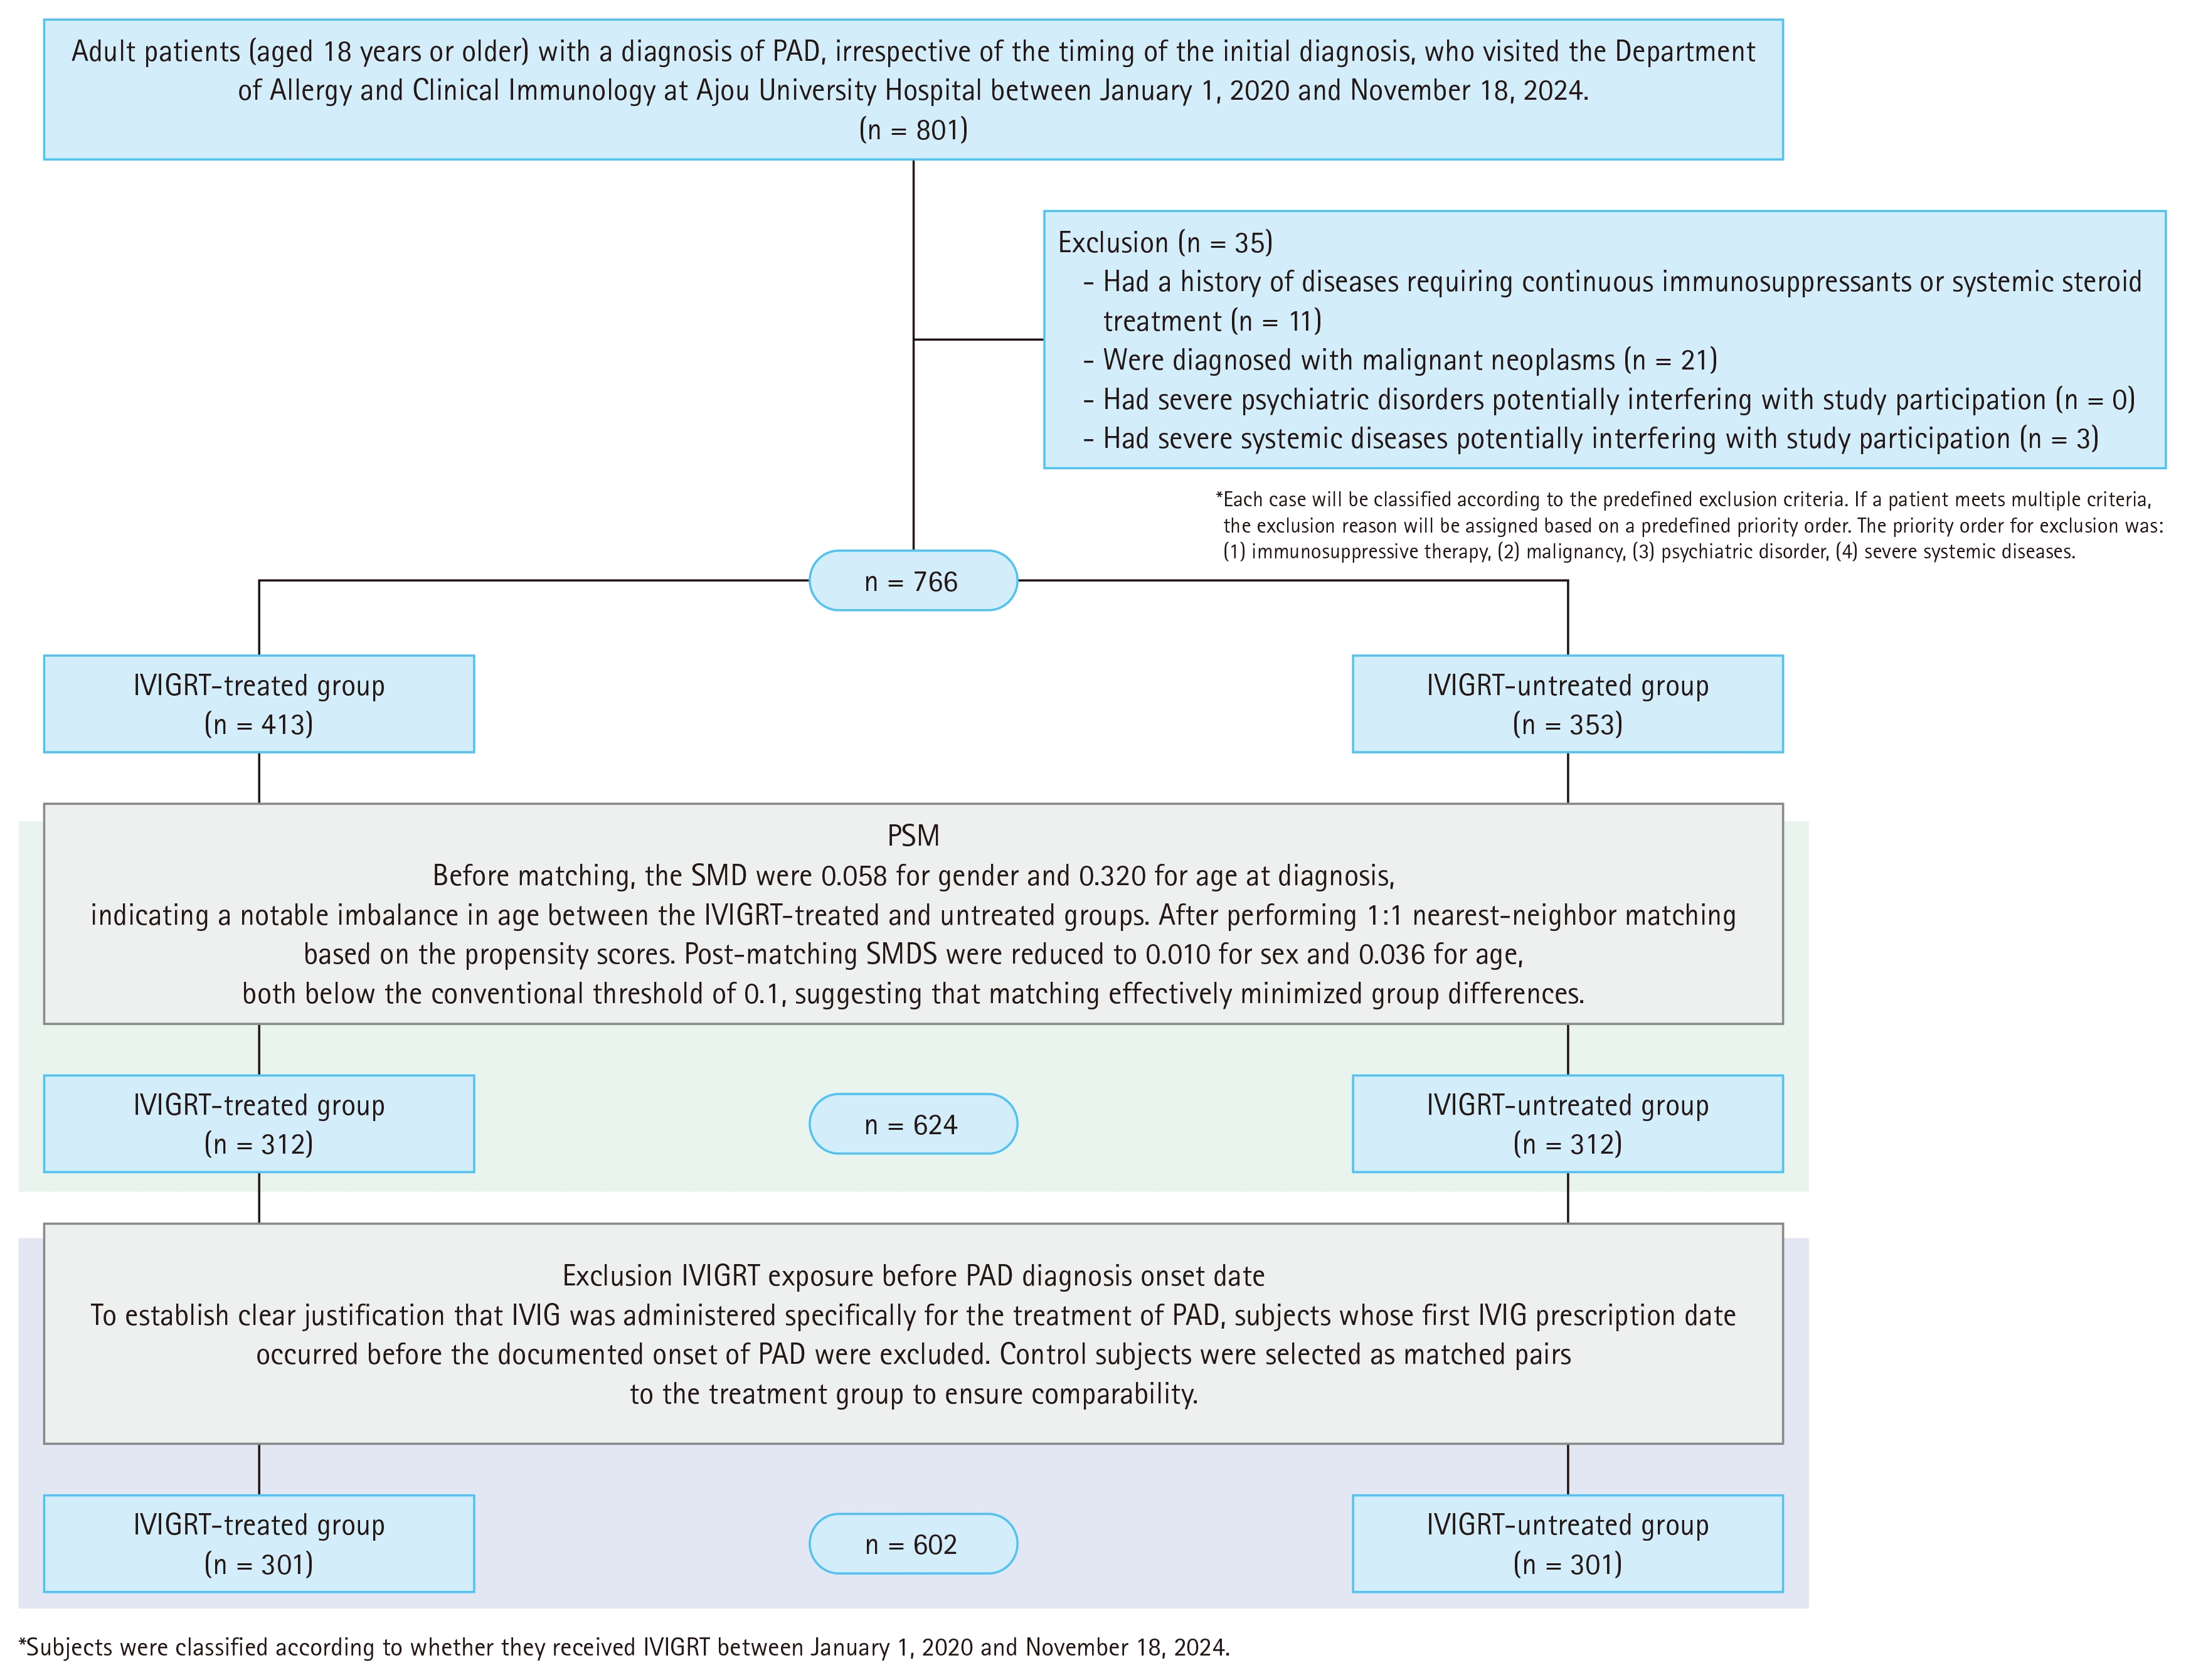
Study participant recruitment. Among 801 adult patients with PAD who visited the Department of Allergy and Clinical Immunology at Ajou University Hospital between January 1, 2020 and November 18, 2024, a total of 766 participants were included in the analysis after excluding 35 patients according to the predefined exclusion criteria. Participants were classified into the IVIGRT-exposed and IVIGRT-unexposed groups based on IVIGRT exposure during the study period. To balance differences in age and sex between the two groups, PSM was performed, resulting in 312 matched participants in each group (n = 624). After excluding participants who had received IVIGRT prior to the onset of PAD diagnosis, the final analysis included 301 participants in the IVIGRT-exposed group and 301 participants in the IVIGRT-unexposed group (n = 602). PAD, primary antibody deficiency; IVIGRT, intravenous immunoglobulin replacement therapy; PSM, propensity score matching; SMD, standardized mean difference.
This study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Board of Ajou University Hospital (AJOUIRB-DB-2024-585). The requirement for informed consent was waived due to the retrospective nature of the study.
Comparison of clinical and laboratory findings
Baseline demographic characteristics, PAD phenotypes, allergic and autoimmune comorbidities, and laboratory parameters were extracted from electronic medical records. Reduced lymphocyte percentage was included as an exploratory hematologic marker because it was available only in a subset of patients due to variations in clinical testing practices. Pneumonia and chronic rhinosinusitis were defined as physician-diagnosed conditions based on clinical and radiologic documentation in the medical records. Multiple chemical sensitivity with sick house syndrome was defined as a physician-documented diagnosis of multisystem symptoms attributed to environmental chemical or indoor exposures [26,27]. Categorical laboratory thresholds were defined according to institutional standards and grouped as follows: type 2 inflammatory markers, including increased total immunoglobulin E (IgE) (> 114 kU/L) and eosinophilia (blood eosinophil count > 150/μL); hematologic markers, including leukopenia (WBC < 4 × 10³/μL) and reduced lymphocyte percentage (< 16%); complement markers, including reduced complement C3 (< 90 mg/dL) and reduced complement C4 (< 10 mg/dL); and autoantibody markers, including thyroglobulin antibody positivity (> 60 U/mL), microsome antibody positivity (>60 U/mL), and rheumatoid factor positivity (> 14 U/mL). Complement C3 and C4 were both assessed; however, only C3 is presented in the Results due to greater data availability and clearer interpretability in this cohort. Quantitative IG and IgG subclass levels were measured using nephelometry. Cut-offs for total IG and IgG SCDs were defined as values below the lower limits of the institutional reference ranges, in accordance with established criteria [12,13]. The institutional reference ranges (updated July 1, 2022) were: IgG 700–1,600 mg/dL; IgA 70–400 mg/dL; IgM 40–230 mg/dL; IgG1 382.4–928.6 mg/dL; IgG2 241.8–700.3 mg/dL; IgG3 21.8–176.1 mg/dL; and IgG4 3.9–86.4 mg/dL [23]. IgG subclass values obtained before July 1, 2022 were originally reported in mg/L and were converted to mg/dL (mg/dL = mg/L ÷ 10) prior to analysis. All IG subclass values were standardized to mg/dL to ensure consistency, including application within the scoring system. Quantitative IgG, IgA, and IgM deficiencies were defined as serum levels below the lower limits of their respective reference ranges. IgG deficiency and hypogammaglobulinemia were analyzed as distinct categories: IgG deficiency was defined by reduced total IgG alone, whereas hypogammaglobulinemia reflected broader global IG reduction involving multiple major IG isotypes. IgGSCD was defined as a serum subclass level below the corresponding reference range.
Ajou-PAD scoring
The Ajou-PAD score was adapted from previously published frameworks [20,21] and comprised symptom- and laboratory- based components (Supplementary Table 1). The reference ranges in Supplementary Table 1 reflect the original laboratory reporting format, whereas all analyses and score calculations in the main manuscript were performed using converted mg/dL values. This scoring system was applied to the final matched cohort to evaluate its association with real-world IVIGRT exposure, with higher scores indicating greater clinical severity and more pronounced humoral IG impairment. The Ajou-PAD score was calculable in 589 of 602 patients with complete data. Discriminative performance of the Ajou-PAD score for IVIGRT exposure was assessed using receiver operating characteristic (ROC) curve analysis, and the optimal cut-off value was determined using the Youden J index [28]. As the Ajou-PAD score is an integer-based discrete scoring system, the ROC-derived cut-off of 9.5 represents the boundary between adjacent score categories. Accordingly, a threshold of ≥ 10 was used to classify patients into higher- and lower-score groups for exploratory analyses and the clinical and laboratory characteristics were compared between these two groups.
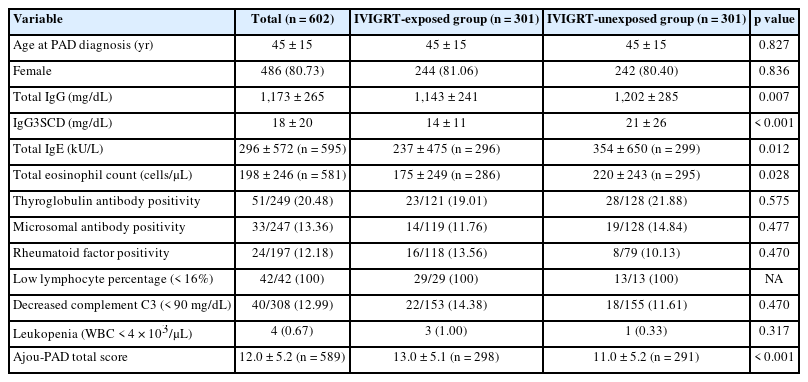
Comparison of demographic, laboratory, and Ajou-PAD score parameters between the two study groups
Statistical analysis
Continuous variables are presented as mean ± standard deviation with corresponding sample size, and categorical variables as number (percentage) or n/N (%) when denominators differed due to missing data. Continuous variables were compared using Student’s t-test, and categorical variables using Pearson’s chi-square test. Univariable logistic regression was performed to identify factors associated with IVIGRT exposure and higher Ajou-PAD score categories. ROC analysis was used to assess the discriminative performance of the Ajou-PAD score for IVIGRT exposure, with the optimal cut-off determined using the Youden J index. A two-sided p value < 0.05 was considered statistically significant. Missing data were handled using complete case analysis, and sample sizes are reported for each variable.
RESULTS
Comparison of clinical characteristics and PAD phenotypes between the IVIGRT-exposed and IVIGRT-unexposed groups
A total of 801 adults were screened, of whom 766 met the eligibility criteria. After propensity score matching by age and sex and exclusion of 22 patients who received IVIGRT before PAD diagnosis, 602 patients were included in the final analytic cohort (301 in each group) (Fig. 1). Among PAD phenotypes, IgG3SCD was the most prevalent phenotype (68.60%), followed by IgG2SCD (10.30%), IgG deficiency (9.63%), IgG4SCD (6.48%), IgA deficiency (4.65%), and hypogammaglobulinemia (4.32%) (Fig. 2). Comparison of these prevalence rates between the two groups showed that IgG3SCD was significantly more prevalent in the IVIGRT- exposed group (81.06%) than in the IVIGRT-unexposed group (56.15%; p < 0.001). Moreover, prevalence rates of IgG deficiency, IgG4SCD, hypogammaglobulinemia, and IgA deficiency were significantly higher in the IVIGRT-exposed group than those in the IVIGRT-unexposed group (p < 0.05 for all), whereas no significant differences were observed in the prevalence of IgG1SCD or IgG2SCD. Among the IVIGRT-exposed patients, the mean annual IVIGRT dose was 107 ± 67 g/year, and the mean dosing interval was 2.50 ± 1.40 months. Overall, the combination rates of IgG3SCD with other quantitative Ig abnormalities were higher in the IVIGRT-exposed group than those in the IVIGRT-unexposed group.
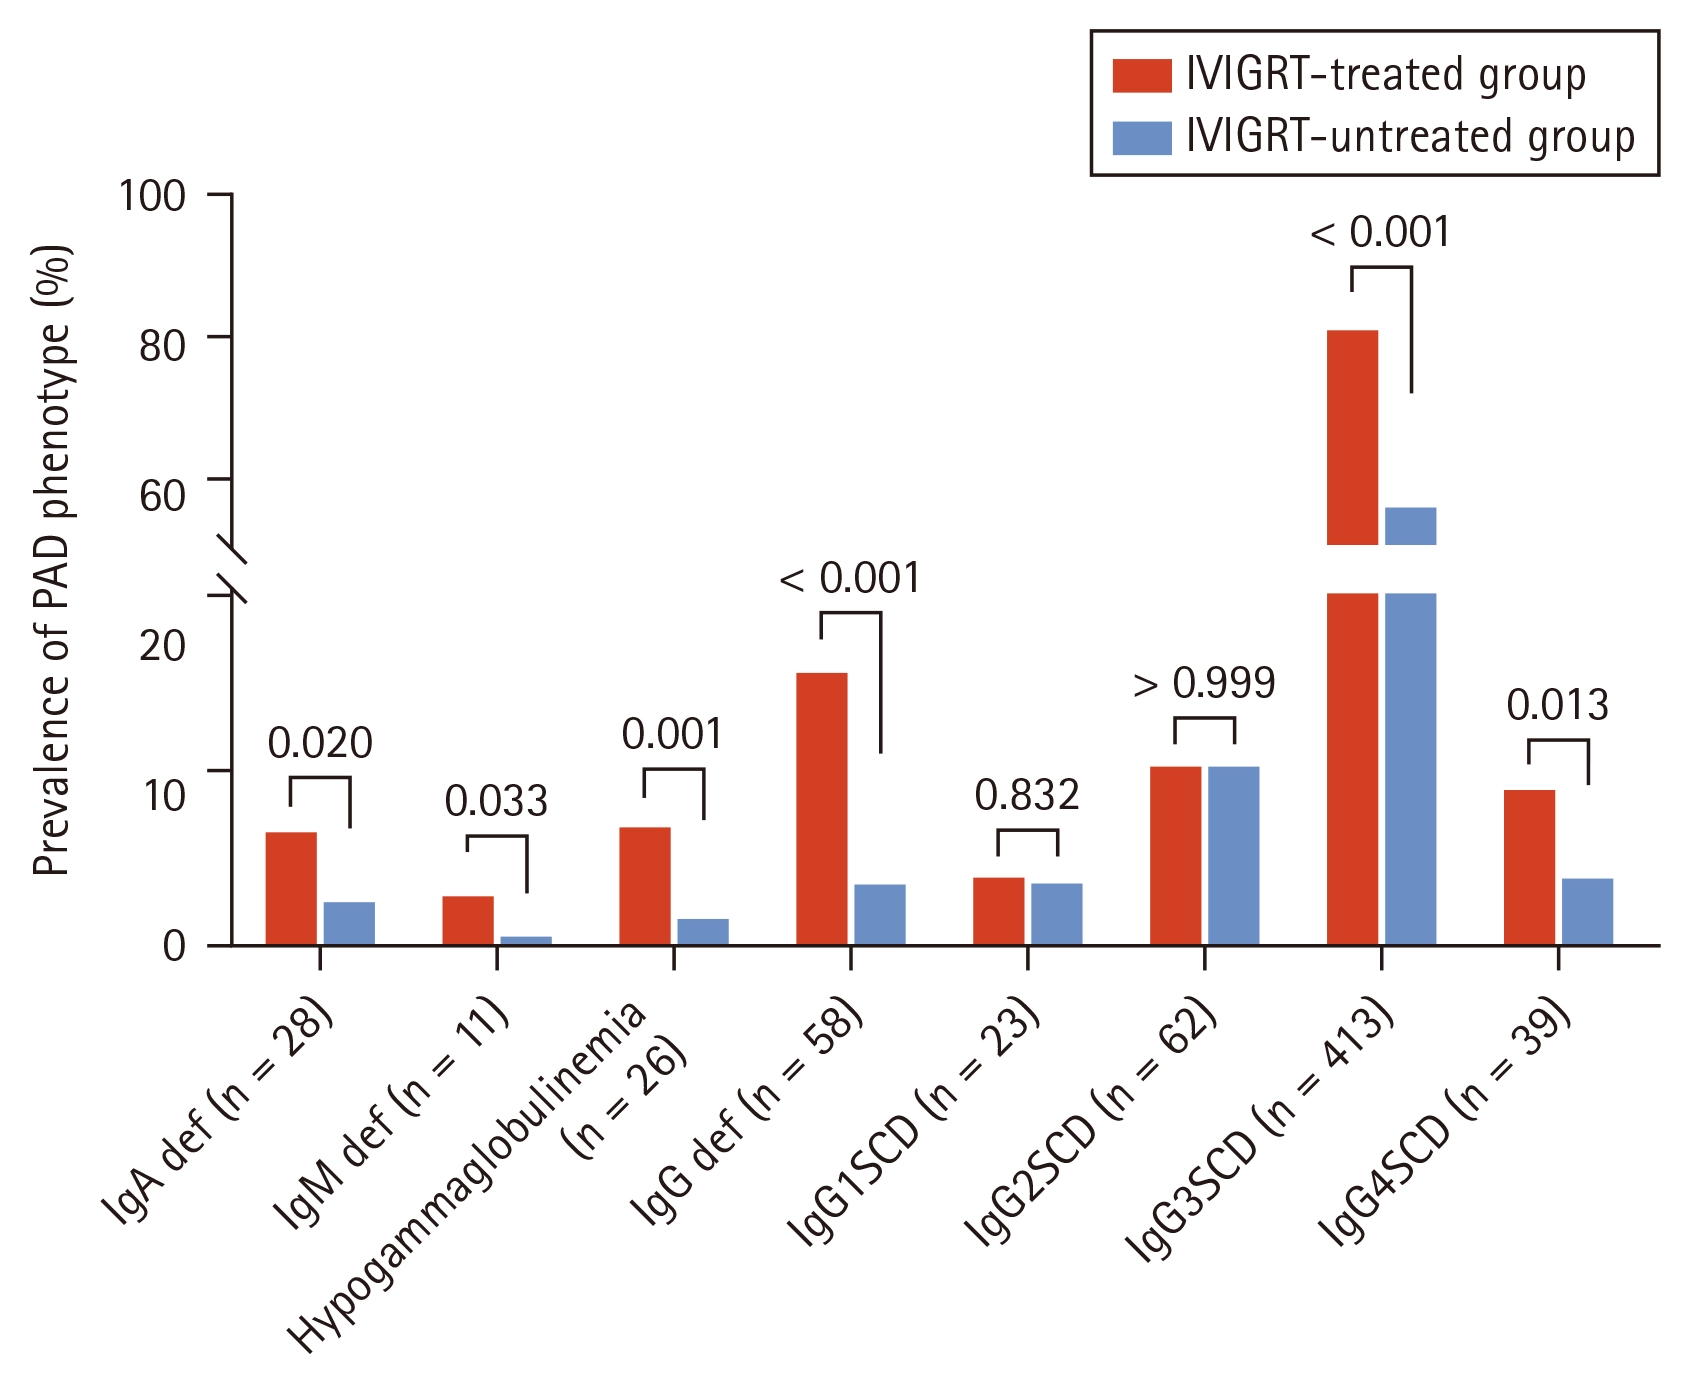
Comparison of PAD prevalence between IVIGRT-exposed and IVIGRT-unexposed groups. The bars represent the prevalence (%) of major PAD phenotypes in the IVIGRT-exposed and IVIGRT-unexposed groups. PAD phenotypes include IgA deficiency, IgM deficiency, hypogammaglobulinemia, IgG deficiency, and IgG SCD (IgG1–IgG4). p values were calculated using the Pearson chi-square test for categorical variables. p values of p < 0.05 were considered statistically significant. PAD, primary antibody deficiency; IVIGRT, intravenous immunoglobulin replacement therapy; IG, immunoglobulin; SCD, subclass deficiency.
Comparison of laboratory parameters between the IVIGRT-exposed and IVIGRTunexposed groups
Comparison of age at PAD diagnosis, sex distribution, Ajou- PAD total score, and laboratory parameters between the two study groups revealed no significant differences in age or sex (Table 1). The mean Ajou-PAD total score was higher in the IVIGRT-exposed group than that in the IVIGRT-unexposed group (13.0 ± 5.1 vs. 11.0 ± 5.2, p < 0.001). However, total IgG and IgG3 levels were significantly lower in the IVIGRT-exposed group than those in the IVIGRT-unexposed group (IgG: 1,143 ± 241 vs. 1,202 ± 285 mg/dL, p = 0.007; IgG3: 14 ± 11 vs. 21 ± 26 mg/dL, p < 0.001). Type 2 inflammatory markers, including serum total IgE and blood eosinophil counts, were lower in the IVIGRT-exposed group than in the IVIGRT-unexposed group (serum total IgE: 237 ± 475 vs. 354 ± 650 kU/L, p = 0.012; blood eosinophil counts: 175 ± 249 vs. 220 ± 243 cells/μL, p = 0.028).
The prevalence of leukopenia (WBC < 4 × 10³/μL) was low and did not differ between the two study groups (1.00% vs. 0.33%, p = 0.317). All patients with available lymphocyte percentage data (n = 42; 29 exposed and 13 unexposed) exhibited reduced lymphocyte percentage (< 16%); therefore, a between-group comparison was not performed (Table 1). Reduced complement C3 levels (< 90 mg/dL) and autoantibody positivity (thyroglobulin antibody > 60 U/mL, microsome antibody >60 U/mL, and/or rheumatoid factor > 14 U/mL) were comparable between the two groups (p > 0.05 for all). Overall, IG levels and type 2 inflammatory markers were lower in the IVIGRT-exposed group, whereas no differences were observed in complement levels or autoantibody positivity between the two groups.
Comparison of allergic and autoimmune comorbidities
Table 2 summarizes the allergic and autoimmune comorbidities between the IVIGRT-exposed and IVIGRT-unexposed groups. The IVIGRT-exposed group displayed a higher prevalence of allergic rhinitis (66.78% vs. 54.82%, p = 0.003), bronchial asthma (46.18% vs. 36.88%, p = 0.021), multiple chemical sensitivity (including sick house syndrome) (14.62% vs. 2.66%, p < 0.001), allergic contact dermatitis (22.92% vs. 15.28%, p = 0.017), thyroid disease (11.63% vs. 2.99%, p < 0.001), rheumatoid arthritis (18.60% vs. 6.31%, p < 0.001), and polycystic ovary syndrome with oral contraceptive use (4.65% vs. 1.33%, p = 0.017) than the IVIGRT-unexposed group. Overall, allergic and autoimmune comorbidities were more frequent in the IVIGRT-exposed group than in the IVIGRT-unexposed group.
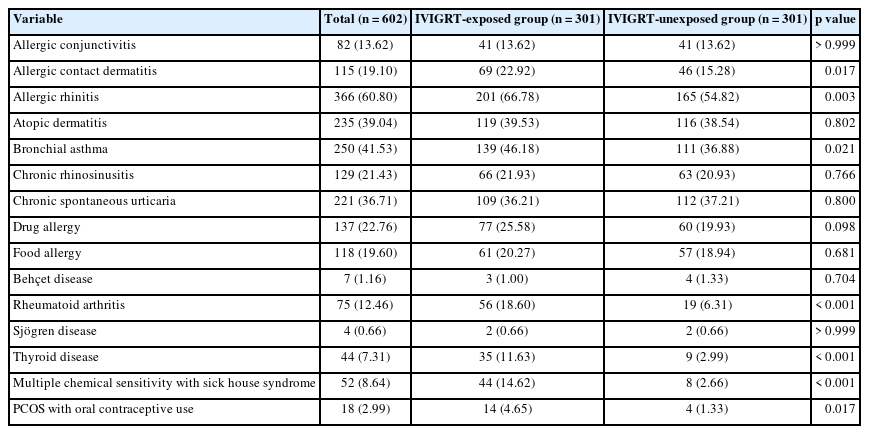
Comparison of comorbid allergic and autoimmune conditions between the two study groups
Factors associated with IVIGRT exposure
Table 3 presents PAD phenotypes associated with IVIGRT exposure based on univariable logistic regression analyses. IgA deficiency (odds ratio [OR] = 2.607, p = 0.025), hypogammaglobulinemia (OR = 4.440, p = 0.003), IgG deficiency (OR = 4.878, p < 0.001), IgG3SCD (OR = 3.344, p < 0.001), and IgG4SCD (OR = 2.373, p = 0.015) were significantly associated with IVIGRT exposure, whereas age, sex, IgG1SCD, and IgG2SCD were not. Analysis of the combinations of two PAD phenotypes showed that combined IgG deficiency and IgG3SCD showed the highest OR for IVIGRT exposure (OR = 12.23, p < 0.001), followed by IgG3SCD plus IgG4SCD (OR = 7.84, p = 0.007), and IgG deficiency plus hypogammaglobulinemia (OR = 4.21, p = 0.005).
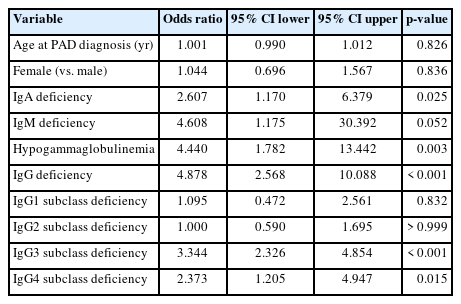
Univariable logistic regression analyses of factors associated with IVIGRT exposure
Table 4 presents allergic and autoimmune comorbidities associated with IVIGRT exposure in the study participants. Allergic rhinitis (OR = 1.657, p = 0.003), bronchial asthma (OR = 1.469, p = 0.021), multiple chemical sensitivity (including sick house syndrome) (OR = 6.270, p < 0.001), allergic contact dermatitis (OR = 1.649, p = 0.018), thyroid disease (OR = 4.269, p < 0.001), rheumatoid arthritis (OR = 3.392, p < 0.001), and polycystic ovary syndrome/oral contraceptive use (OR = 3.622, p = 0.025) were significantly associated with IVIGRT exposure, whereas chronic rhinosinusitis, atopic dermatitis, chronic spontaneous urticaria, drug allergy, food allergy, Sjögren disease, and Behçet disease were not. Overall, IgG3SCD (alone or in combination with other quantitative Ig abnormalities) and allergic/autoimmune comorbidities were associated with IVIGRT exposure.
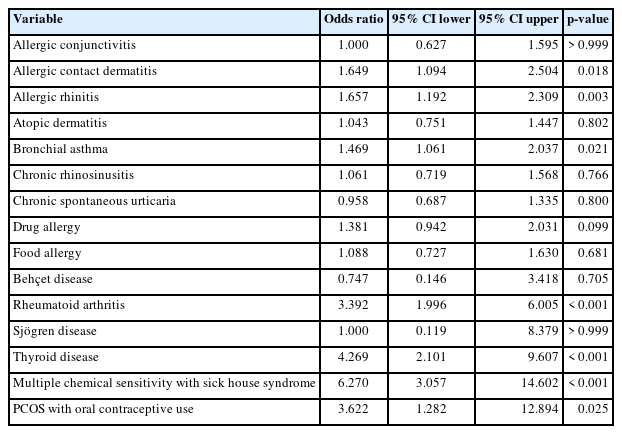
Univariable logistic regression analyses of comorbidities associated with IVIGRT exposure
Ajou-PAD score performance for IVIGRT exposure
The Ajou-PAD score demonstrated modest discriminatory performance for IVIGRT exposure (area under the curve [AUC] = 0.61; 95% confidence interval [CI], 0.56–0.65; p < 0.001) (Fig. 3A). Using the Youden J index, we identified an optimal cut-off value of 9.5 with a sensitivity of 0.74 and a specificity of 0.44 (Fig. 3B). Based on this threshold, we categorized patients into higher-score (the Ajou-PAD score ≥ 10) and lower-score (< 10) groups, comprising 64.86% and 35.14% of the 589 patients with available Ajou-PAD score data, respectively (Fig. 3C). Compared to the lower-score group, the higher-score group exhibited higher prevalence rates of IgA deficiency (7.07% vs. 0.48%, p < 0.001), hypogammaglobulinemia (6.54% vs. 0.48%, p = 0.001), IgG deficiency (13.87% vs. 2.42%, p < 0.001), and IgG2SCD (12.30% vs. 5.80%, p = 0.012). Other PAD phenotypes did not differ significantly between the groups (Table 5). These findings were supported by univariable logistic regression analyses, in which IgA deficiency (OR = 15.67, p = 0.007), hypogammaglobulinemia (OR = 14.43, p = 0.009), IgG deficiency (OR = 6.51, p < 0.001), and IgG2SCD (OR = 2.28, p = 0.014) were associated with the higher-score group (data not shown). Among comorbidities, chronic rhinosinusitis was positively associated with the higher-score group (OR = 1.61, p = 0.031), whereas atopic dermatitis was inversely associated with the higher-score group (OR = 0.69, p = 0.033) (data not shown). Overall, an Ajou-PAD score of ≥ 10 classified 382 (64.86%) of the 589 patients into the higher-score group and was associated with distinct immunologic characteristics.
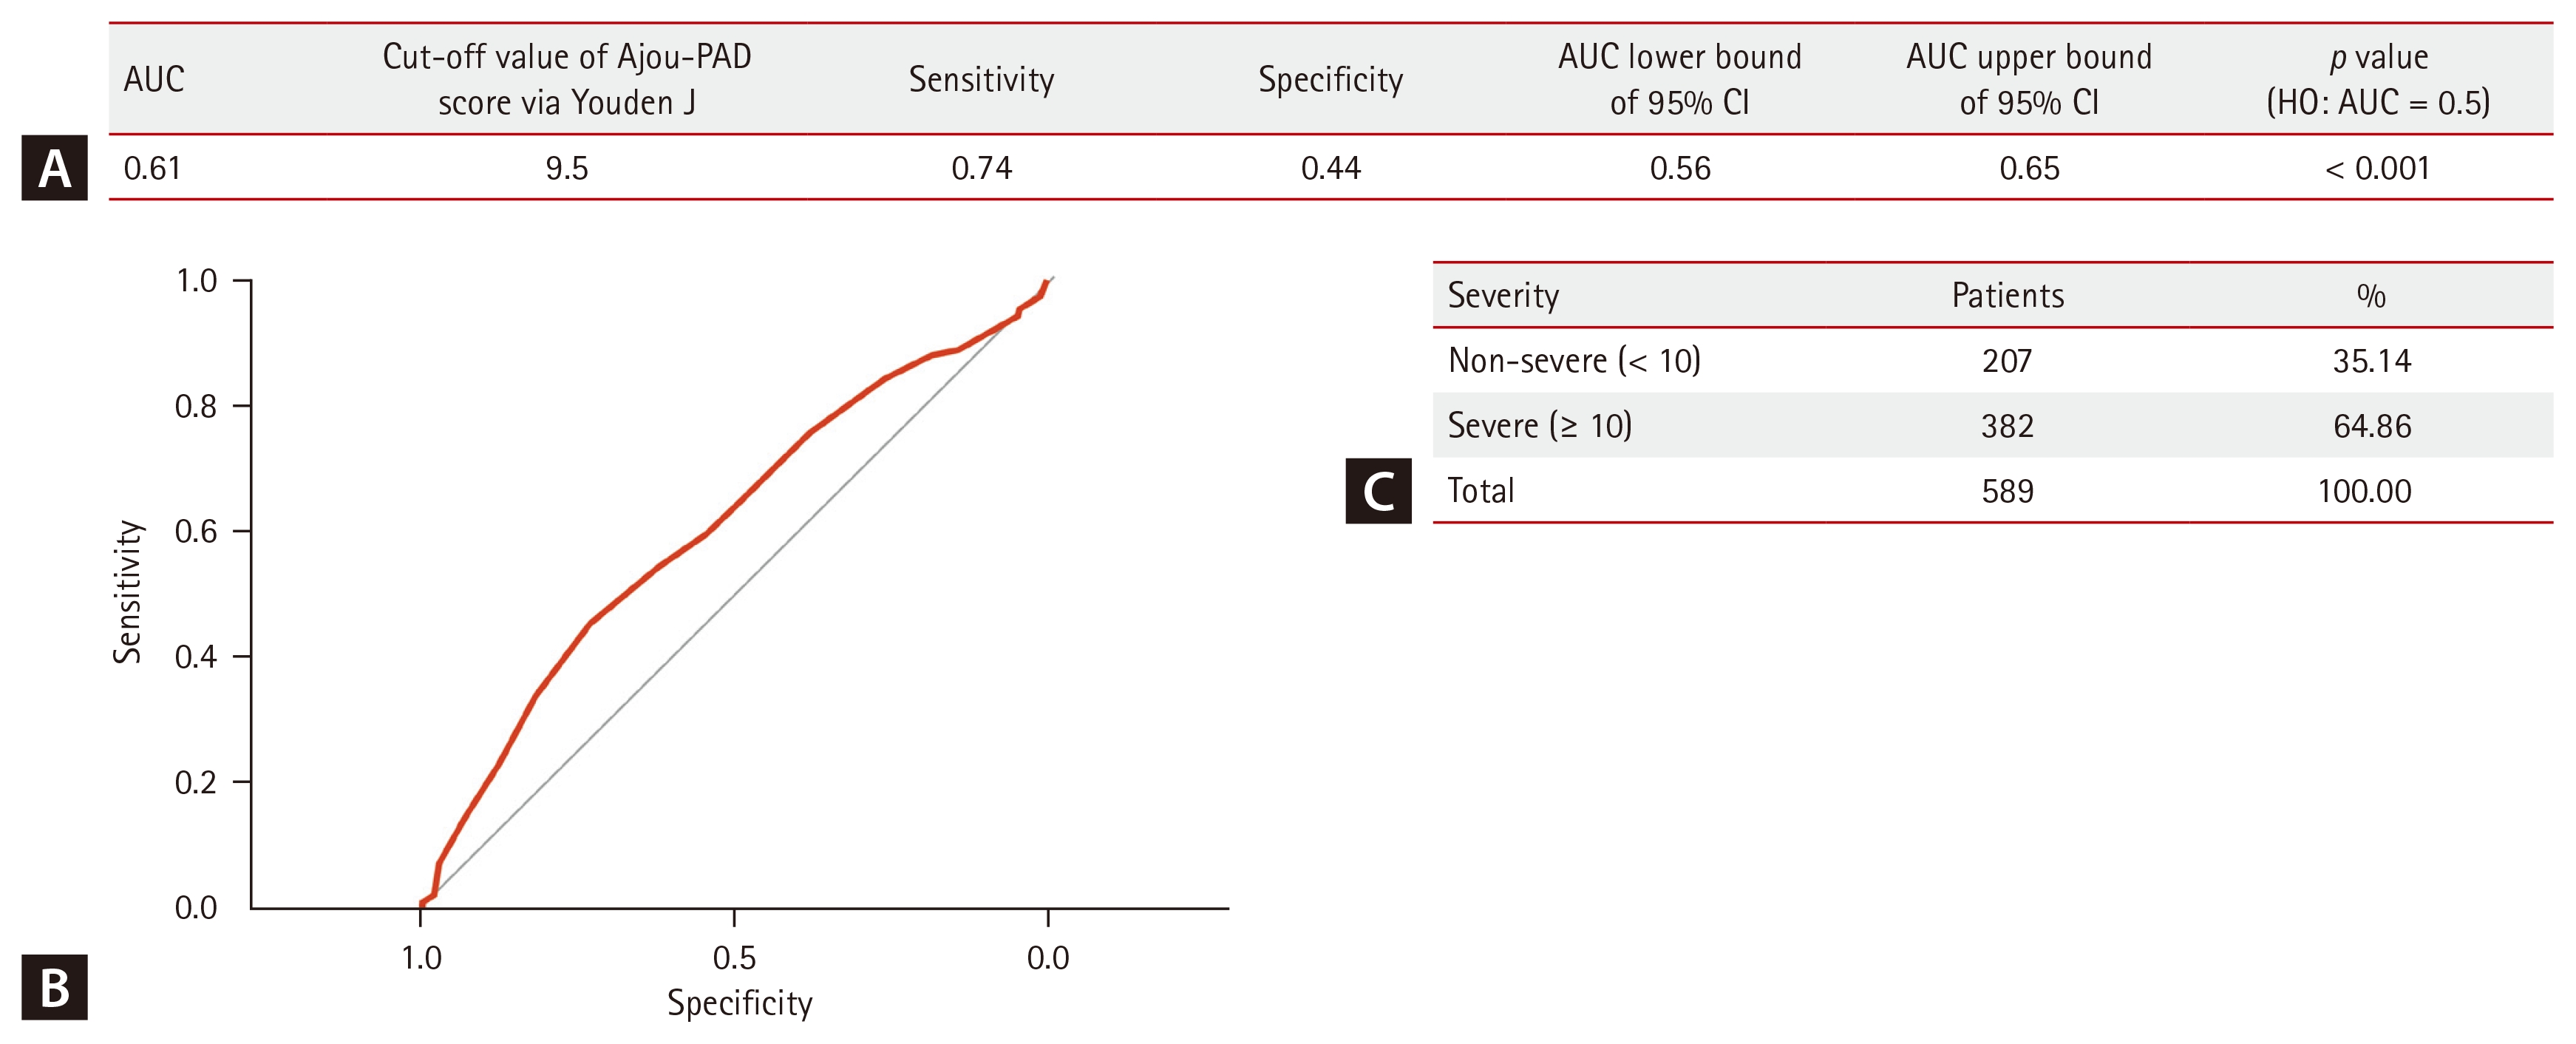
Ajou-PAD Score for discriminating IVIGRT exposure. (A) ROC curve representing the discriminative performance of the Ajou- PAD score for IVIGRT exposure. The AUC was 0.61 (95% CI, 0.562–0.653), which was significantly different from the null hypothesis of an AUC of 0.5 (p < 0.001). (B) The optimal cut-off value of the Ajou-PAD score determined using the Youden J index was 9.5, yielding a sensitivity of 0.738 and a specificity of 0.443. (C) Based on an Ajou-PAD score threshold of 10, study participants were classified into lower-score (< 10) and higher-score (≥ 10) groups. Of the total 589 participants with available score data, 382 (64.86%) were classified as higher-score and 207 (35.14%) as lower-score. PAD, primary antibody deficiency; IVIGRT, intravenous immunoglobulin replacement therapy; ROC, receiver operating characteristic; AUC, area under the curve; CI, confidence interval.
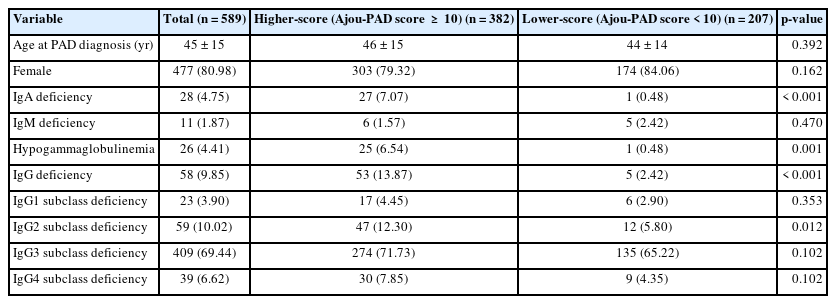
Comparison of baseline clinical and lab findings between the higher-score and lower-score groups based on the Ajou-PAD score
DISCUSSION
In this study, we compared clinical characteristics, laboratory findings, and allergic/autoimmune comorbidities according to IVIGRT exposure in adult patients with PAD. The IVIGRT-exposed group showed a higher prevalence of IgG3SCD, IgG deficiency, and combined deficiency phenotypes, as well as a higher prevalence of allergic and autoimmune comorbidities. In univariable analyses, IgG3SCD, hypogammaglobulinemia, and other quantitative IG abnormalities were associated with IVIGRT exposure. The Ajou- PAD score showed modest discriminatory performance for IVIGRT exposure.
In this adult Korean cohort, IgG3SCD was the most prevalent PAD phenotype, consistent with previous studies in similar populations [29–31]. Adult patients with IgG3SCD have been reported to experience recurrent respiratory infections and more frequent asthma exacerbations, and IVIGRT may be beneficial in selected cases [8,16,29]. We observed a significant association between IgG3SCD and IVIGRT exposure, which was more pronounced when IgG3SCD coexisted with other quantitative IgG deficiency or IgGSCD phenotypes. These findings highlight the importance of assessing both total IG levels and IgG subclasses in characterizing PAD phenotypes and understanding treatment patterns associated with IVIGRT in adult patients with PAD in clinical practice.
In this study, the IVIGRT-exposed group exhibited significantly higher prevalence rates of allergic and autoimmune comorbidities than those in the IVIGRT-unexposed group. Although allergic rhinitis and bronchial asthma were more frequent in the IVIGRT-exposed group, their serum total IgE levels and blood eosinophil counts were lower. These findings are consistent with the clinical observation that a subset of adult patients with PAD present with infection-dominant airway disease rather than type 2-driven inflammation [16,32,33]. This pattern suggests that some asthma patients with PAD may present a mixed inflammatory phenotype, in which IVIGRT has been reported to be associated with reduced infection burden in selected populations. Chronic rhinosinusitis is a heterogeneous inflammatory disease with evolving treatment approaches, including biologics [34]. In addition, the present study revealed higher comorbid rates of multiple chemical sensitivity and allergic contact dermatitis in the IVIGRT-exposed group than in the IVIGRT-unexposed group, although multiple chemical sensitivity has been described as a multisystem condition with proposed neuroimmune mechanisms [26,27] and allergic contact dermatitis is mediated by T cell-mediated responses. Autoimmune thyroid disease and rheumatoid arthritis were also significantly associated with IVIGRT exposure, consistent with previous reports that autoimmune manifestations are common in inborn errors of immunity [15,35]. Autoimmune thyroid disease and rheumatoid arthritis are common autoimmune diseases in our population (Table 4). Taken together, these findings support a close association between PAD and higher comorbid rates of major allergic and autoimmune diseases, although further investigations are needed to clarify pathogenic mechanisms and whether and which sub-phenotype of PAD could be refined according to comorbidity profiles. Evaluation for multiple chemical sensitivity and autoimmune comorbidities (including autoimmune thyroid disease), as well as common allergic diseases such as asthma and rhinitis, may be relevant considerations in the clinical evaluation of adult PAD patients.
IVIGRT is widely used as a therapeutic option for patients with PAD and has been suggested to reduce infection burden and exert immunomodulatory effects [18,36,37]. Nevertheless, the optimal timing, dose, duration, and objective biomarkers for initiating and maintaining IVIGRT are not fully understood across PAD phenotypes and clinical contexts, and relevant considerations continue to evolve [19,38,39]. Several decision-support approaches have already been proposed, including severity scoring systems originally developed for PIDs and applied to support chronic management decisions [20,21]. The present study evaluated the Ajou-PAD score (integrating clinical and immunologic findings) in a large cohort of adult PAD patients and observed modest discriminatory performance for IVIGRT exposure. These findings suggest that the Ajou-PAD score may reflect real-world treatment decisions; however, its clinical utility remains limited and requires further validation.
This study has several limitations. First, the retrospective, single-center design may limit generalizability, and the tertiary referral setting may have enriched for patients with airway and allergic comorbidities. IVIGRT initiation was determined by treating physicians, introducing potential confounding by indication and selection bias. In addition, the IVIGRT-exposed group included both patients who received a single IVIGRT course and those who underwent repeated or long-term treatment, which may have introduced exposure heterogeneity and potential misclassification bias. Therefore, our findings should be interpreted as describing real-world treatment patterns associated with IVIGRT exposure rather than causal treatment effects. Second, functional antibody assessments, such as vaccine response testing and specific antibody measurements, were not routinely performed in this cohort [40]. Further prospective multicenter studies with standardized immunologic evaluation are needed to validate these findings and refine sub-phenotype classifications in adults with PAD.
In conclusion, IgG3SCD was the most prevalent PAD phenotype in this cohort and was more frequently observed among patients receiving IVIGRT in routine clinical practice. The Ajou-PAD score showed modest discriminatory performance for IVIGRT exposure and should be considered an exploratory adjunct rather than a standalone tool for treatment decision-making.
KEY MESSAGE
1. IgG3SCD was the most prevalent PAD phenotype and was more frequently observed among Korean adults with PAD receiving IVIGRT in routine clinical practice.
2. The Ajou-PAD score showed modest discriminatory performance for IVIGRT exposure and may reflect real-world treatment decisions.
Notes
Acknowledgments
The authors thank the Clinical Trial Center of Ajou University Medical Center for their support in coordinating and administrating this clinical research.
CRedit authorship contributions
Jung-Eun Han: investigation, writing - original draft, visualization; Hyun young Lee: data curation, formal analysis; Haeng Jun Kim: writing - review & editing, visualization; Yoo Seob Shin: investigation; Yeong-Min Ye: investigation; Hae-Sim Park: conceptualization, writing - review & editing, supervision, funding acquisition
Conflicts of interest
The authors disclose no conflicts.
Funding
This research was supported by grant from the Korea Health Technology R&D Project (RS-2024-00439277) through the Korean Health Industry Development Institute, funded by the Ministry of Health and Welfare.